
A Baker’s cyst, also called a popliteal cyst, is a fluid-filled sac that forms behind the knee and is usually felt as a lump, swelling or tightness at the back of the knee. It develops when an underlying knee problem, such as osteoarthritis or a meniscus tear, makes the joint produce extra fluid, which collects in a pocket at the back of the knee. Baker’s cysts are common, are generally harmless and tend to settle when the underlying knee problem is treated.
Key Takeaways
- A Baker’s cyst is a fluid-filled pocket behind the knee, usually driven by an underlying knee problem such as osteoarthritis or a meniscus tear.
- The cyst itself is generally harmless and tends to fill and empty as the knee flares up and settles.
- Ultrasound can confirm a cyst, while MRI is the gold standard and also shows what is causing it.
- Treating the underlying knee problem matters more than draining the cyst, which often refills.
- Sudden calf pain or swelling needs same-day medical care, because a ruptured cyst and a DVT can look alike.
Every other day at MTP Health, patients present with concerns about being diagnosed with a Baker’s cyst or popliteal cyst. Understandably, finding out you have a “cyst” in your knee sounds bad. The good news is they really are harmless. They can be annoying and a little uncomfortable at times, but there is no further “damage” occurring due to their existence.
Baker’s cysts are commonly found alongside intra-articular knee disorders such as osteoarthritis and meniscus tears. They can occur at any age and vary in size: smaller cysts may cause no symptoms, while larger ones are more likely to be symptomatic. Treatment typically involves treating the underlying cause, sometimes draining the fluid from the cyst, and in some cases surgery to remove the cyst.
Below, we cover how Baker’s cysts develop, how they are diagnosed and the treatment options, because understanding the condition absolutely improves confidence.
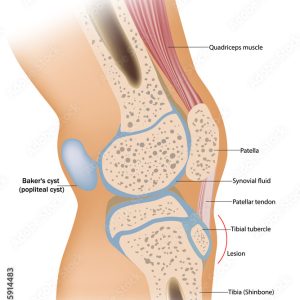
A Simple Way to Picture a Baker’s Cyst
Imagine for a moment you have a blister on your foot or hand. It is very annoying, but only temporary. The blister is the byproduct of some other aggravation, such as rubbing or an overload incident. The skin responds by becoming distended as fluid fills under the irritated area. When the irritation settles and the fluid goes, you are left with a slightly loose patch of skin.
A Baker’s cyst is that distended pocket, filled with fluid. Unlike a blister, it doesn’t go away; it stays after the fluid has gone. So the next time your knee gets a little aggravated, the excess fluid fills the loose pocket at the back of the knee, and it feels like something is blocking the back of the knee. When the irritation settles, the fluid goes away and the knee returns to feeling more normal again.
Because the cyst fills and empties, it is normal to have good and bad times. Rest assured it will settle back to normal and won’t be doing any damage in the meantime.
The cyst filling is just the symptom. To reduce the annoyance of a Baker’s cyst, the aim should be to address whatever is irritating the knee and causing the extra fluid. Address the cause and things will feel better.
What are 3 things that increase your risk of developing it?
Several factors may increase your risk of developing a Baker’s cyst:
- Arthritis: Arthritis is a common cause of Baker’s cysts, particularly knee osteoarthritis and rheumatoid arthritis. These conditions cause the joint to create excess fluid, which can lead to the formation of a cyst.
- Other knee conditions: Meniscus tears, cartilage damage or ACL tears can cause excess fluid in the knee joint, which may increase the risk of developing a Baker’s cyst.
- Age: The risk may be higher in adults, as the risk of knee conditions such as arthritis increases with age.
What are some common signs and symptoms of a Baker’s cyst?
Baker’s cysts can appear suddenly, or progress and get worse over time. Common signs and symptoms include:
- Vague pain behind the knee
- Swelling or a lump at the back of the knee
- Reduced range of motion, particularly struggling to fully bend or straighten the knee
- Tightness or stiffness behind the knee that can worsen with activity
Other conditions can cause similar symptoms, so it is always worth having pain behind the knee checked by a healthcare professional.

What Tests or Imaging Help Diagnose a Baker’s Cyst?
Several tests and imaging studies may be used to help diagnose a Baker’s cyst:
- Ultrasound: Ultrasound uses sound waves to create images of the inside of the body. It shows the cyst and surrounding tissues, along with its size and shape. It is non-invasive and involves no radiation, which makes it a good screening tool. The downside is that it can be difficult to tell a popliteal cyst apart from a meniscal cyst or myxoid tumour.
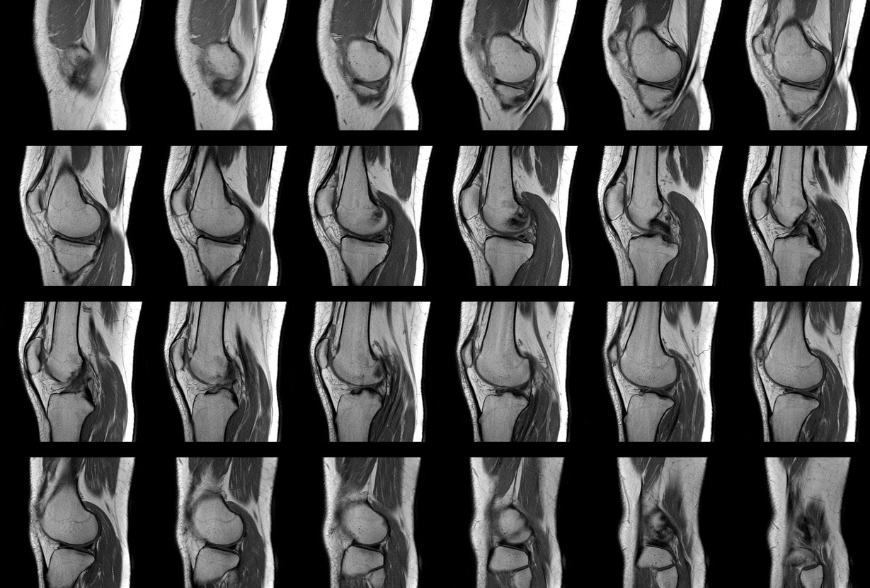
- MRI: An MRI (magnetic resonance imaging) scan uses powerful magnets and radio waves to create detailed images of the inside of the body. It is considered the gold standard for diagnosing a Baker’s cyst, because it shows soft tissue abnormalities and can also diagnose other problems inside the knee. The downside is cost.
- X-ray: An X-ray shows the bones of the knee joint and can rule out other conditions that cause similar symptoms, such as a bone tumour or fracture.
What are some common differential diagnosis options for Bakers cysts?
Several conditions can cause similar symptoms to a Baker’s cyst and may need to be ruled out:
- Deep vein thrombosis (DVT): A blood clot in the deep veins of the lower leg, which can cause swelling and pain behind the knee. This is a serious condition. A physiotherapist can assess for it and refer you on if a DVT is suspected.
- Popliteal artery entrapment syndrome: The popliteal artery, which supplies blood to the lower leg, becomes compressed or trapped, causing pain and swelling behind the knee. It isn’t common, but a physiotherapist can refer you on if it is suspected.
- Ligament or tendon injury: Several ligaments and tendons at the back of the knee can be injured and cause swelling and pain, so a thorough assessment is needed to pinpoint which one.
- Calf strain: A tear in the calf muscle from overstretching or increased load. Strains high in the calf can feel as though they are behind the knee.
- Osteoarthritis: A degenerative joint condition that can cause swelling and pain in the knee. Further assessment and sometimes imaging is needed to confirm it.
- Rheumatoid arthritis: An autoimmune disorder that causes joint inflammation, including in the knee, and can cause swelling and pain behind the knee.
These are just a few of the possibilities, and the conditions considered depend on your individual case, so a healthcare professional is the right person to work out the cause of pain behind the knee.
When to Worry About a Lump Behind the Knee
Most lumps behind the knee turn out to be a Baker’s cyst, but some signs need checking sooner.
Seek urgent medical care the same day if you have:
- Sudden pain, swelling, warmth or redness in the calf, which can be a ruptured cyst or a DVT and needs a doctor to tell them apart
- Shortness of breath or chest pain alongside leg swelling (call triple zero (000))
- A lump behind the knee that is hot and red, or comes with a fever or feeling unwell
- A lower leg or foot that turns pale, cold, numb or weak
Book an assessment if:
- The lump is growing, feels hard, or does not change in size from day to day
- A lump appeared without any known knee problem or injury
- Pain behind the knee lasts more than a few weeks or limits bending, squatting or walking
- Your knee locks, catches or gives way
- Swelling keeps returning after activity
A physiotherapist can assess the knee, arrange imaging where needed and refer you on if something other than a Baker’s cyst is suspected.
Is there any evidence for PRP injection, Cortisone injections or Shockwave treatments for this?
The evidence for these treatments in Baker’s cysts is limited, and none of them is recommended as a first-line treatment on its own.
PRP Injections
PRP injections involve injecting a concentrated solution of platelets, a type of cell involved in healing, into the affected area. They are designed to stimulate healing and reduce inflammation, but there is limited evidence for their use in Baker’s cysts specifically.
Shockwave Therapy
Shockwave therapy uses high-energy sound waves to stimulate healing in the affected area. Again, the evidence that it helps Baker’s cysts is limited, so it is not recommended as a first-line treatment.
Cortisone Injections
Cortisone is an anti-inflammatory medication that can be injected to reduce inflammation and pain. It can provide short-term relief of Baker’s cyst symptoms, but it does not fix the underlying issue, which is ultimately what will make your knee feel better. How long the relief lasts differs between patients, and your healthcare professional can advise whether it is appropriate for you.
None of these treatments works for everyone. The right option depends on the severity of your condition and your overall health, and more research is needed to fully understand their effectiveness and risks for Baker’s cysts.
What is a typical timeline for recovery from a Baker’s Cyst?
Recovery can take anywhere from a few weeks to a few months, depending on the severity of the condition and the management plan. If the underlying issue is not addressed, the Baker’s cyst will continue to cause symptoms.
In general, recovery may involve:
- Rest: Initially, it may help to rest the affected leg and avoid activities that cause pain or discomfort.
- Ice: Applying ice to the area can help reduce swelling and inflammation.
- Physiotherapy and exercise physiology: In the early stages, physiotherapy can teach you exercises to strengthen the muscles around the knee and improve range of motion, and exercise physiology can progress that strength work over the longer term.
- Medications: Over-the-counter or prescription medications, such as nonsteroidal anti-inflammatory drugs (NSAIDs) or paracetamol, may be used to reduce inflammation and pain.
- Drainage: If the cyst is large or causing significant discomfort, the fluid can usually be drained with a needle and syringe. This gives temporary relief, but if the cause of the cyst is not addressed, it is likely to return.
Can I rupture a Baker’s Cyst myself? If so, is this dangerous?
It is possible to rupture a Baker’s cyst, but it is not common. The cyst is separated from the joint by a thin wall of tissue. If the cyst becomes very large, that wall can become stretched and thin, which could lead to a rupture.
When a Baker’s cyst ruptures, the fluid can leak into the surrounding tissues, such as the calf. This can cause sudden pain, swelling and sometimes bruising around the ankle, which can look very similar to a DVT, so it needs medical assessment to tell the two apart. Rarely, a large cyst can also press on nearby veins and contribute to a DVT.
Normal activities such as walking or moving the leg generally won’t rupture a Baker’s cyst. However, a large cyst with a thin wall can rupture on its own. If this happens, seek medical attention as soon as possible.
Is there any harm in continuing to exercise/move without specific treatment for a Baker’s Cyst?
If you keep exercising without treatment, the cyst could become larger and cause more pain and discomfort. Pressure from the cyst can also irritate surrounding tissues and structures, potentially leading to further injury. In some cases, as discussed above, a cyst can rupture and cause sudden pain and swelling, which may affect your ability to exercise.
Baker’s cysts are also often linked to underlying knee conditions such as arthritis, which can worsen over time if left untreated. Addressing these conditions helps prevent long-term damage to the joint. Where knee arthritis is driving the cyst, our Osteoarthritis Clinic focuses on treating the joint itself. A healthcare professional can give you specific advice on treatment and activity changes to manage your symptoms and protect your knee.
Getting Help for a Baker’s Cyst
If a lump behind your knee keeps coming back or is getting in the way of your day, the aim is to settle whatever is irritating the knee, not just the cyst. At MTP Health, physiotherapists, exercise physiologists and orthopaedic surgeons work under one roof. Your knee can be assessed, treated and, if it is ever needed, reviewed by a specialist without starting again elsewhere. You can book an appointment directly, with no referral needed.
Frequently Asked Questions (FAQs)
1. What is a Baker’s cyst?
A Baker’s cyst, or popliteal cyst, is a pocket of joint fluid that bulges into the back of the knee, felt as a lump, swelling or tightness. It is usually caused by an underlying knee problem such as osteoarthritis or a meniscus tear. It is generally harmless and tends to settle once that underlying problem is treated.
Disclaimer: This article is general information only and does not take into account your personal objectives, situation or needs. It is not a substitute for individual assessment by a qualified health professional, who is the right person to speak with before acting on anything described here.
Recent Post
-
Why Do Your Joints Ache in Menopause, and What Helps?
Key Takeaways Falling and fluctuating oestrogen around perimenopause and menopause can leave joints stiff and…
-
Inflammatory Joint Pain: Psoriatic Arthritis and Other Causes
Key Takeaways Inflammatory joint pain is usually stiffest after rest, eases with movement and affects…
-
How Much Does Shoulder Surgery Cost in Australia?
Key Takeaways Public care as a public patient carries no direct cost for the surgery,…
-
Cortisone Injection for Shoulder Pain: Does It Actually Work?
Key Takeaways A cortisone injection settles inflammation and eases pain for a period, but it…
-
Shoulder Pain at Night: Why It Worsens and When to Act
Key Takeaways Lying down loads the shoulder differently and removes the daytime movement that masks…
-
Wrist Pain on the Little Finger Side: TFCC Injuries
Wrist pain on the little-finger side is often a TFCC injury. Learn the signs, why it clicks on rotation, physio-first care and when arthroscopy helps.
-
Wrist Pain After a Fall on an Outstretched Hand
Sore wrist after a fall on an outstretched hand? How to tell a scaphoid fracture, ligament sprain and distal radius fracture apart, and what to do next.
-
Stiff Elbow After a Fracture: Why It Won’t Straighten
Elbow still won’t straighten after a fracture? Why post-fracture stiffness happens, how the rehab window works and when arthroscopic release is considered.
-
A Pop at the Elbow When Lifting: Distal Biceps Rupture
A sudden pop at the elbow when lifting may be a distal biceps rupture. Learn the signs, why the first weeks matter, and repair versus rehab options.
-
Numb Ring and Little Finger: Cubital Tunnel Syndrome
Numb ring and little finger, worse with a bent elbow or at night? Learn the signs of cubital tunnel syndrome and how MTP Health treats it.


