
Thanks for tuning in to another episode of empowering insights.
The concept of functional to structural decline is what we feel really helps to separate us from other rehab providers. We regularly get comments like “I’ve exercise before, but not like this” when people come to see us. This is the kind of experience that becomes a regular feeling when you are doing exercise that is perfectly catered to where you are at that time. And that’s really what the movement Hierachy is all about.
Show notes:
- What the difference between an acute injury and functional decline is [and why most injuries occur as a result of movement].
- Why gradual ramp-ups in pain are so common.
- Why looking for ONE specific cause may not be super helpful.
- The concept of the Movement Hierarchy (See images below).
- How to use the movement hierarchy to clearly lay out the plan for where your health and movement is headed.
- Where most people get it wrong when it comes to their own movement & fitness (Hint: the answer will challenge you).
- What you can do if you experience random flare-ups such as back pain.
- Why you should start treating your mind and body as the same thing when it comes to rehab & fitness.
- Plenty, more!
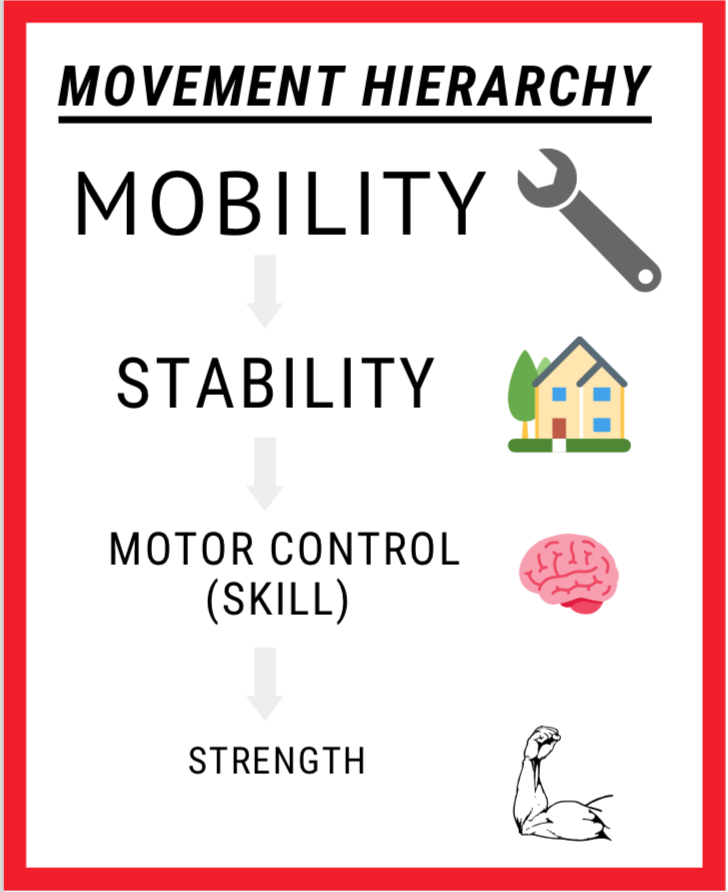
BONUS: See where the movement hierarchy applies to your current training regime
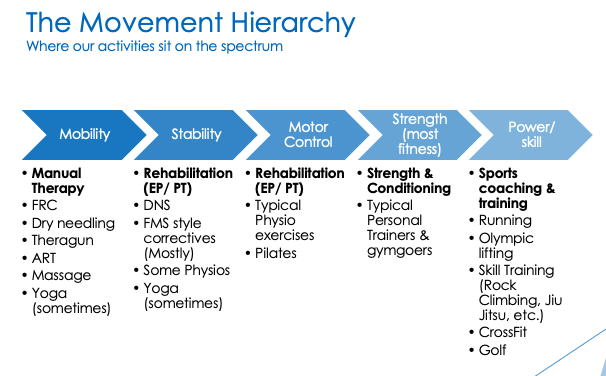
- Most people start way too far on the right-hand side of the Movement Hierarchy spectrum.
- This leads to all sorts of problems if they don’t have the proper pre-requisites from the lower ends of the hierarchy.
- Each stage in the hierarchy is essentially a progression from the one before it (left to right) in increasing order of complexity.
- Not everyone will need to focus on the elements to the left of the movement hierarchy, however, as a general rule of thumb, those who have not been active in a number of years or lack a STRONG base of athletic preparation will need to address some of these elements.
- If addressed early enough in the process these elements can be quite simple & easy to take care of.
- A person does not need to stop doing all other exercise to address components at any end of the spectrum, they simply need to intelligently modify and manage themselves effectively.
To see a detailed, scientific breakdown of the movement hierarchy, along with practical recommendations, check out our comprehensive article HERE
Recent Post
-
Knee Osteotomy: The Surgery That Can Delay a Knee Replacement for Younger Patients
Key Takeaways Knee osteotomy realigns the leg so body weight passes through healthier cartilage, easing…
-
What Is Sciatica and Why Does It Run Down My Leg?
Key Takeaways Sciatica describes pain that starts in the lower back or buttock and travels…
-
Kneecap Dislocation Surgery: When Is MPFL Reconstruction Needed?
Key Takeaways A first kneecap dislocation is usually managed without surgery, with reduction, imaging and…
-
Driving After Knee Replacement, Kneeling and Walking Timeline
Key Takeaways Driving after knee replacement usually resumes once you can brake firmly without hesitation…
-
Best Orthopaedic Surgeon in Sydney: How to Choose the Right One for You
Key Takeaways There is no official ranking of the “best orthopaedic surgeon in Sydney”. Treat…
-
Hip Resurfacing Recovery: When Can You Return to the Gym?
Key Takeaways Returning to the gym happens in stages, with rehabilitation exercises, cycling and controlled…
-
What Happens If Hip Resurfacing Fails? Revision Surgery Explained
Key Takeaways Pain, swelling, clicking, or a limp do not automatically mean hip resurfacing has…
-
Can Women Have Hip Resurfacing? Understanding Who Is Suitable
Key Takeaways Women can be suitable for hip resurfacing, but eligibility depends more on component…
-
Hip Resurfacing vs Hip Replacement: Which Lasts Longer for Younger Patients?
Key Takeaways Neither procedure automatically lasts longer; the best option depends on anatomy, bone quality,…
-
How Long Does an Anterior Hip Replacement Last? Implant Lifespan Explained
Key Takeaways Modern anterior hip replacements commonly remain unrevised for 20 years or longer, although…


